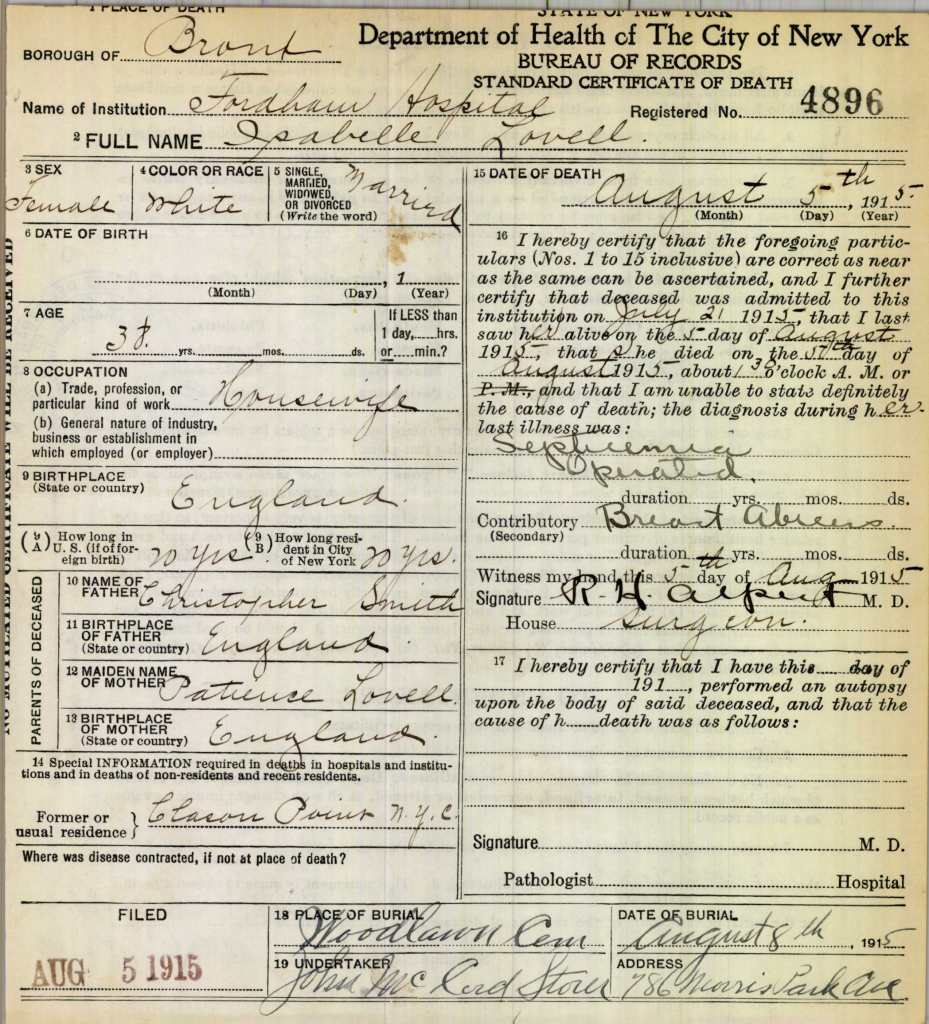
STATE OF NEW YORK Department of Health of The City of New York BUREAU OF RECORDS STANDARD CERTIFICATE OF DEATH
1 PLACE OF DEATH: BOROUGH OF Bronx
Name of Institution: Fordham Hospital
Registered No. 4896
2 FULL NAME: Isabelle Lovell
3 SEX: Female
4 COLOR OR RACE: White
5 SINGLE, MARRIED, WIDOWED, OR DIVORCED: Married
6 DATE OF BIRTH: [Blank]
7 AGE: 38 yrs.
8 OCCUPATION: (a) Trade, profession, or particular kind of work: Housewife
9 BIRTHPLACE: England
9(A) How long in U.S. (if of foreign birth): 20 yrs
9(B) How long resident in City of New York: 20 yrs
PARENTS OF DECEASED
10 NAME OF FATHER: Christopher Smith
11 BIRTHPLACE OF FATHER: England
12 MAIDEN NAME OF MOTHER: Patience Lovell
13 BIRTHPLACE OF MOTHER: England
14 Special INFORMATION required in deaths in hospitals and institutions and in deaths of non-residents and recent residents. Former or usual residence: Clason Point N.Y.C.
15 DATE OF DEATH: August 5th, 1915
16 I hereby certify that the foregoing particulars (Nos. 1 to 15 inclusive) are correct as near as the same can be ascertained, and I further certify that deceased was admitted to this institution on July 21 1915, that I last saw her alive on the 5 day of August 1915, that she died on the 5th day of August 1915, about 3 o’clock A.M., and that I am unable to state definitely the cause of death; the diagnosis during her last illness was: Septicemia Operated Contributory (Secondary): Breast Abscess Witness my hand this 5 day of Aug 1915 Signature: R. H. Alpert M.D. House Surgeon
17 [Blank]
FILED: AUG 5 1915
18 PLACE OF BURIAL: Woodlawn Cem DATE OF BURIAL: August 8th 1915
19 UNDERTAKER: John McCord Stow ADDRESS: 786 Morris Park Ave


